

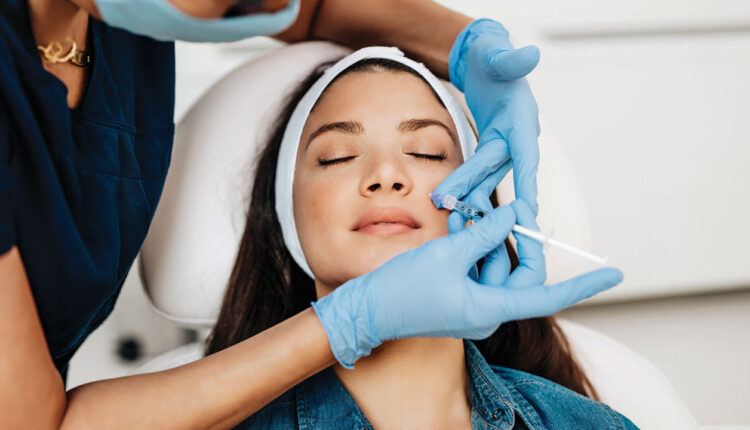
The New Frontier of Dermal Fillers
From facial esthetics to emerging periodontal applications, dermal fillers may offer oral health professionals new ways to address tissue volume, facial harmony, and patient esthetic concerns.
This course was published in the September/October 2026 issue and expires October 2029. The authors have no commercial conflicts of interest to disclose. This 2 credit hour self-study activity is electronically mediated.
AGD Subject Code: 780
EDUCATIONAL OBJECTIVES
After reading this course, the participant should be able to:
- Identify the applications and benefits of dermal fillers.
- List the risks involved in administering dermal fillers.
- Discuss how dermal filler application may fit into the dental hygienist’s scope of practice.
Part two of a two-part series. Part one appears in the July/August 2026 issue.
Dentistry has long played a central role in facial esthetics. From full-mouth reconstruction, whitening, smile makeovers, to the integration of cosmetic procedures, such as neuromodulators and dermal fillers, oral health professionals routinely influence facial form, balance, and function. Despite the natural alignment of dentistry and esthetics, the incorporation of dermal fillers into dental practice is sometimes viewed as unconventional or even outside traditional boundaries. However, with their extensive knowledge of facial anatomy, oral health professionals are ideal providers to administer dermal fillers.
As fillers continue to evolve, particularly in tissue regeneration and collagen stimulation, their applicability in dentistry may increase both in cosmetic and periodontal procedures. The integration of dermal fillers may represent not a departure from dentistry, rather an extension of its long-standing commitment to comprehensive, patient-centered care.1
Mechanism of Action for Dermal Fillers
Second only to botulinum toxin type A neuromodulators, dermal fillers rank among the most requested treatments in the esthetic industry, offering the ability to restore lost volume, enhance contours, and support overall facial harmony.2 Unlike botulinum toxin type A neuromodulators that reduce wrinkles by inhibiting muscle contraction, dermal fillers can reduce wrinkles and improve skin texture by restoring volume loss.
Dermal fillers, like neuromodulators, are also injected, but not directly into muscle. Instead, dermal fillers are injected into or beneath the skin to add volume and enhance facial structures. By restoring volume to select areas, they can create the appearance of fuller, smoother, and more supple skin.2
Dermal fillers vary in viscosity and clinical purpose. Common components include hyaluronic acid (HA), calcium hydroxylapatite, and biostimulatory polymers such as poly-L-lactic acid (PLLA) and polycaprolactone (PCL).3 Hyaluronic fillers are hydrophilic and restore volume by attracting and binding to water molecules, increasing water retention, tissue hydration, and structural support. These fillers are widely used to enhance facial contours, such as cheeks, lips, and chin, providing both immediate volumizing effects and subtle lifting while smoothing lines and wrinkles.3
Beyond simple volume augmentation, PLLA and PCL fillers demonstrate biostimulatory effects, promoting neocollagenesis and longer-term tissue regeneration in soft tissues. This regenerative potential has expanded their clinical relevance beyond esthetic enhancement into applications aimed at facial form and function.4
Applications of Dermal Fillers
Dermal fillers with biostimulant properties promote collagen production and influence tissue quality at a cellular level. Gingival recession is a challenging condition due to limited restorative treatment options. In addition to esthetic concerns, recession frequently results in dentinal hypersensitivity, which may make routine dental hygiene care uncomfortable for patients. Even with topical remineralizing or desensitizing agents, many patients continue to experience sensitivity issues that impact their overall oral care experience.3
Evidence in periodontal literature suggests that HA plays an active role in wound healing and regeneration, enhancing periodontal parameters when used adjunctively with traditional periodontal therapy.5 Moreover, some clinical data indicate potential benefits of HA in reducing probing depths and improving clinical attachment levels in recession and periodontal defects.6
The regenerative properties of specific dermal fillers, particularly those designed to stimulate collagen synthesis, offer a promising adjunctive approach in managing tissue volume loss. Injecting such fillers into the gingiva where recession is present may restore tissue contour, improve the gingival margin profile, and support underlying periodontal structures.3 While formal clinical trials specifically investigating filler injections for the purpose of reversing gingival recession are emerging, the biologic rationale parallels how HA supports extracellular matrix modulation that guides tissue cell growth and healing.6
Dermal fillers are also being explored for interdental use by injecting filler directly into the interdental papilla to correct flattened or blunted papillae following periodontal therapy. By restoring tissue height and volume, dental hygienists can address both esthetic and functional outcomes, promoting improved gingival architecture without compromising tissue appearance. This approach offers a unique opportunity to complement traditional periodontal therapy, enhancing patient satisfaction and supporting comprehensive treatment goals that prioritize both tissue health and facial esthetics.3
Esthetic Enhancements
Beyond gingival applications, dermal fillers play a critical role in comprehensive facial esthetics that support intraoral restorative and cosmetic procedures. Dermal fillers complement esthetic and restorative dentistry by restoring extraoral tissue volume and supporting facial structures that directly influence the appearance and balance of a patient’s smile.
Patients who invest in veneers, orthodontics, or comprehensive smile makeovers may still be dissatisfied with subtle age-related changes, such as thinning lips, hollowed cheeks, or downward-turning smile lines caused by loss of soft tissue volume and collagen.2 Addressing these extraoral factors allows clinicians to offer a truly comprehensive smile restoration that considers the teeth, soft tissues, and surrounding facial framework as interconnected elements of esthetics.
These fillers are not only used to restore volume but also to enhance overall facial balance and proportion. Strategic placement can subtly adjust facial contours, supporting esthetic outcomes that complement restorative or cosmetic dental procedures. For example, adding volume to the chin can help elongate the jawline and soften the appearance of a Class II occlusion profile, improving lower-face balance. Conversely, carefully augmenting the nasal area can create visual harmony for patients with a Class III occlusion profile, softening concavities and enhancing midface proportion. By thoughtfully applying dermal fillers in this way, clinicians can provide a more balanced and youthful facial contour, ultimately supporting the esthetic results of restorative and cosmetic treatments.2
Beyond volume and proportion, dermal fillers can also improve lip hydration, enhance midface fullness, and subtly lift areas affected by age-related soft tissue loss. These enhancements not only contribute to facial harmony but also reinforce the esthetic outcomes of intraoral procedures, ensuring that the patient’s smile appears natural and integrated with the surrounding facial tissues. When incorporated thoughtfully into dental practice, dermal fillers allow clinicians to deliver a patient-centered approach that treats the face holistically improving appearance while supporting patient confidence and satisfaction.2
Adverse Reactions and Medical Emergencies
While dermal fillers offer significant esthetic and functional benefits, their administration carries an inherent risk that demands heightened clinical vigilance. Because fillers are typically delivered using larger-gauge needles and placed into deeper tissue planes than neuromodulators or when administering local anesthetics, the potential for serious adverse events, including vascular compromise, is increased.2
Clinicians must possess a comprehensive understanding of facial anatomy, appropriate injection depth, product selection, volume control, aspiration techniques, and expected diffusion profiles. Additionally, safe administration of dermal fillers also requires a strong foundation in pathophysiology and pharmacology, along with careful review of the patient’s medical history, to identify contraindications and prevent adverse reactions or allergic responses. Failure to account for these factors can jeopardize patient safety and outcomes.2 Although many complications, such as bruising, resolve over time, others can lead to permanent tissue damage due to vascular occlusion.
Bruising and Vascular Occlusion
Bruising (ecchymosis) at the injection site is a common and expected outcome of dermal filler procedures, but its severity and duration can vary significantly depending on the patient’s anatomy, the injection technique, and product type. Skilled clinicians can minimize bruising by carefully selecting injection sites that avoid dense vascular regions, using appropriate needle or cannula sizes, controlling injection depth, and moderating the volume and speed of product delivery. Pre- and post-procedure measures also play a key role: patients should avoid anticoagulant or antiplatelet medications when medically safe, limit alcohol and certain supplements that increase bleeding risk, and apply cold compresses immediately after treatment to reduce capillary damage and inflammation.2
Additionally, patient-specific factors, such as age, skin thickness, and vascular fragility, should be considered during treatment planning. Gentle handling of soft tissues, precise anatomical knowledge, and real-time assessment during injection can help further reduce the risk of significant bruising.
Vascular occlusion is a rare but serious complication, potentially leading to tissue ischemia, necrosis, or vision loss without prompt treatment. A systematic review of vascular occlusion following filler injections confirms that anatomical regions with complex vasculature, such as the glabella, nose, and nasolabial folds, are most frequently implicated.7
Clinicians must differentiate between routine bruising and signs of occlusion, which often present with disproportionate pain, pallor, and delayed capillary refill.7,8 Vascular occlusion is very serious and immediate treatment is necessary to avoid permanent damage. Treatment typically involves the administration of hyaluronidase, warm compresses, and gentle massage to break down the occluding filler and restore blood flow and oxygen to the tissues.9,10 However, without immediate treatment, patients have been subjected to unrepairable tissue necrosis and vision loss due to filler occluding the ophthalmic artery.11
Emerging technologies, such as vascular mapping and ultrasound visualization, can assist clinicians in identifying superficial blood vessels, helping to avoid intravascular trauma and further decreasing the likelihood and severity of bruising. Educating patients about expected post-procedure changes, the normal timeline for bruising resolution, and strategies to manage discoloration not only improves safety but also enhances patient confidence and satisfaction with the procedure.2 However, these tools used to enhance visualization of the underlying tissue and vascularity should supplement, not replace, clinical knowledge, advanced training, and sound judgment.
Dental Hygienists’ Preparedness and Practice Integration
While some view the administration of dermal fillers as outside the traditional boundaries of dentistry, dental hygienists possess the combination of anatomical knowledge, clinical judgment, and patient-centered chairside experience necessary to successfully inject dermal fillers. Although several states permit dentists to administer both dermal fillers and neuromodulators, only a small number of states currently authorize dental hygienists to inject dermal fillers or administer neuromodulators.12-17
While scope of practice and the stipulations for the administration of dermal fillers vary considerably from state to state, these regulatory limitations do not reflect the profession’s capabilities. Dermal fillers can be a valuable addition to the dental hygienist’s therapeutic arsenal to better serve their patients.
Dental hygienists are uniquely prepared to contribute to the safe and effective delivery of facial esthetic services. Their foundational education includes training in head and neck anatomy, pharmacology, pain control, and recognition/management of medical emergencies. Combined with hands-on experience administering intraoral injections, monitoring patient responses, and delivering chairside care, dental hygienists bring high-level competence and patient-centered focus to facial esthetic procedures.2
Even where state regulations preclude hygienists from administering fillers themselves, their contributions to facial esthetic services remain substantial. Hygienists can support these procedures through patient intake, education, pre- and post-operative photos, and medical history review. This collaborative approach enhances efficiency, improves patient experience, and allows dental providers to focus on technical aspects of filler administration.
References
- de Castro Costa M, Andrade CA, Dantas RVF, Germani M, Buzalaf MAR, Soares DG. Clinical durability of hyaluronic acid-based dermal fillers for facial application: a systematic review. Aesthetic Plast Surg. 2026;50:1971-1993.
- Maci M, Fanelli C, Lorusso M, Ferrara D, Caroprese M, Laurenziello M, et al. Botulinum toxin type A and hyaluronic acid dermal fillers in dentistry: a systematic review of clinical application and indications. J Clin Med Res. 2024;16:273-283.
- Ruiz-de-León G, Cortés-Eslava D, Hernández-Pacheco E, Serrera-Figallo MÁ, Torres-Lagares D, Baus-Domínguez M. Biopolymers in facial aesthetics: gel-based applications, safety, effectiveness, and future prospects—a systematic review of the literature. Gels. 2025;11:455.
- Haddad S, Galadari H, Patil A, Goldust M, Al Salam S, Guida S. Evaluation of the biostimulatory effects and the level of neocollagenesis of dermal fillers: a review. Int J Dermatol. 2022;61:1284-1288.
- Kalimeri E, Roccuzzo A, Stähli A, et al. Adjunctive use of hyaluronic acid in the treatment of gingival recessions: a systematic review and meta-analysis. Clin Oral Investig. 2024;28:329.
- Malcangi G, Inchingolo AD, Trilli I, Ferrante L, Casamassima L, Nardelli P, et al. Recent use of hyaluronic acid in dental medicine. Materials (Basel). 2025;18:1863.
- Hong GW, Hu H, Chang K, et al. Adverse effects associated with dermal filler treatments: part II vascular complication. Diagnostics (Basel). 2024;14:1555.
- Soares DJ. Bridging a century-old problem: the pathophysiology and molecular mechanisms of HA filler-induced vascular occlusion (FIVO)—implications for therapeutic interventions. Molecules. 2022;27:5398.
- Wang R, Li Y, Li Z, Yao H, Zhai Z. Hyaluronic acid filler-induced vascular occlusion—three case reports and overview of prevention and treatment. J Cosmet Dermatol. 2024;23:1217-1223.
- Fabi SG, Desyatnikova S, Dayan SH. Prevention and management of dermal filler complications: a review. Facial Plast Surg Aesthet Med. 2025;27:120-124.
- Mehta P, Kaplan JB, Zhang-Nunes S. Ischemic complications of dermal fillers. Plast Aesthet Res. 2022;9:57.
- New Mexico. Administration of Botulinum Neurotoxin (Botox) and Dermal Fillers, NM Admin Code § 16.5.14.8. Available at https://www.srca.nm.gov/parts/title16/16.005.0014.html. Accessed August 18, 2026.
- Oregon Board of Dentistry. Scope of Practice. Available at oregon.gov/dentistry/Pages/scope-practice.aspx. Accessed August 18, 2026.
- Permit for the Use of Dermal Fillers and Botulinum Toxin for Dental Use. Available at ndlegis.gov/information/acdata/pdf/20-02-01.pdf. Accessed August 18, 2026.
- State of Alabama. Administration of Botulinum Toxin and Similar Treatments by Dentists. Available at https://dentalboard.org/wp-content/uploads/2024/09/BDEAL-APA3-270-X-2-.25-Administration-of-Botulinum-Toxin-and-Similar-Treatments-by-Dentists.pdf.
- Oklahoma State Board of Dentistry. Advanced Procedures for Dental Hygienists: Neuromodulator Administration. Available at law.cornell.edu/regulations/Oklahoma/OAC-195-15-1-6.1. Accessed August 18 2026.
- Arizona State Dental Board. Recent Rules Approved. Available at https://dentalboard.az.gov/rules. Accessed August 18, 2026.
From Dimensions of Dental Hygiene. September/October 2026; 24(5):32-35



